


Key features
Input Contribution Rate glide path
The ICR glide path represents the Commonwealth's share of funding for public hospital services. Under the ICR glide path, the contribution increases annually:
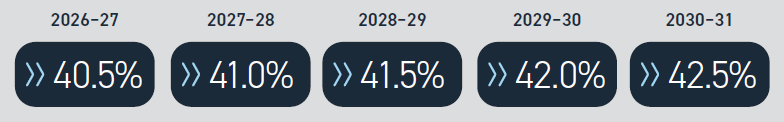
Each State's designated ICR is the greater of the glide path rate; the State's 2025–26 Commonwealth Contribution Rate; or any other specific rate (e.g. 50% for Highly Specialised Therapies).
Funding cap
The Commonwealth's total annual funding contribution for each State under the Addendum will be subject to a funding cap. The funding cap for 2026–27 is based on the 2025–26 final entitlement plus additional amounts under Schedule K – Addendum to the NHR Agreement: Revised Public Hospital Funding and Health
Reform Arrangements 2025–26 (Schedule K) for the one-year extension ($1.701 billion nationally), multiplied by 110.25%. For 2027–28 to 2030–31, the funding cap grows at 8% per annum.
Minimum Funding Guarantee
The Commonwealth will provide a minimum additional $15 billion in funding over the 5 years of the Addendum compared to the maximum amount that States would have received if the 2020–2025 Addendum funding arrangements applied. The NHFB calculates annual State-specific MFG amounts.
Funding streams
The Addendum maintains 3 established funding streams:
- Activity Based Funding (ABF) – based on the number of weighted services provided and the price for delivering those services
- Block funding – based on the efficient cost of providing services such as teaching and training, small rural hospitals, other mental health and highly specialised therapies
- Public Health funding – based on the Commonwealth's historical contribution to population health services within each State and Territory. Under the new Addendum this will be transitioned to Block funding.
From 2027–28, a new stream commences:
- Service Model Reform Funding (SMRF) – represents dedicated funding for reform (up to 0.5% of each State's funding cap per year).
Safety and quality
Sentinel Event funding adjustments will continue where episodes are priced at zero National Weighted Activity Units (NWAUs) with the funding adjustment made after the funding cap has been applied. Funding adjustments for Hospital Acquired Complications and Avoidable Hospital Readmissions are paused pending review by the Australian Commission on Safety and Quality in Health Care (due 30 June 2027), with shadow
pricing maintained during this period.
Value
From 2029–30, the Addendum enables value‑based pricing adjustments for low‑value and high-value care. The ACSQHC will develop low‑value and high-value care lists (due 30 June 2028).
